The habits with the best evidence for preventing childhood obesity are family routines that start early: responsive feeding in infancy, enough sleep, water and milk instead of sugary drinks, plenty of active play, and limited screen time. They matter because obesity is common. From 2017 to March 2020, 19.7% of US children and teens aged 2–19 had obesity, about 14.7 million young people (CDC).
Prevention isn't about willpower or putting a child on a diet. It's about the household environment, which parents can shape, and about catching a steep upward trend on the growth chart early.
Why childhood obesity matters
- It tends to persist. In a meta-analysis of 15 cohort studies, about 55% of children with obesity still had obesity as adolescents, and about 80% of adolescents with obesity still had it as adults (Simmonds 2016).
- Fatty liver disease is common. About 34% of children attending obesity clinics had fatty liver disease in a meta-analysis, compared with about 8% of children in general-population studies (Anderson 2015). The condition was then called NAFLD and is now called MASLD (metabolic dysfunction-associated steatotic liver disease).
- It raises other health risks. The AAP notes that untreated obesity is linked with serious short- and long-term problems, including cardiovascular disease and type 2 diabetes (AAP).
Age matters too. In a US study of 854 people followed from birth, children with obesity at age 1–2 who had no parent with obesity were at low risk of adult obesity (8%). Among older children, obesity became an increasingly strong predictor regardless of their parents' weight (Whitaker 1997). So a chubby baby isn't a cause for alarm, but a school-age child whose BMI keeps climbing deserves attention. To see where your child stands, look up the healthy weight range for their height.
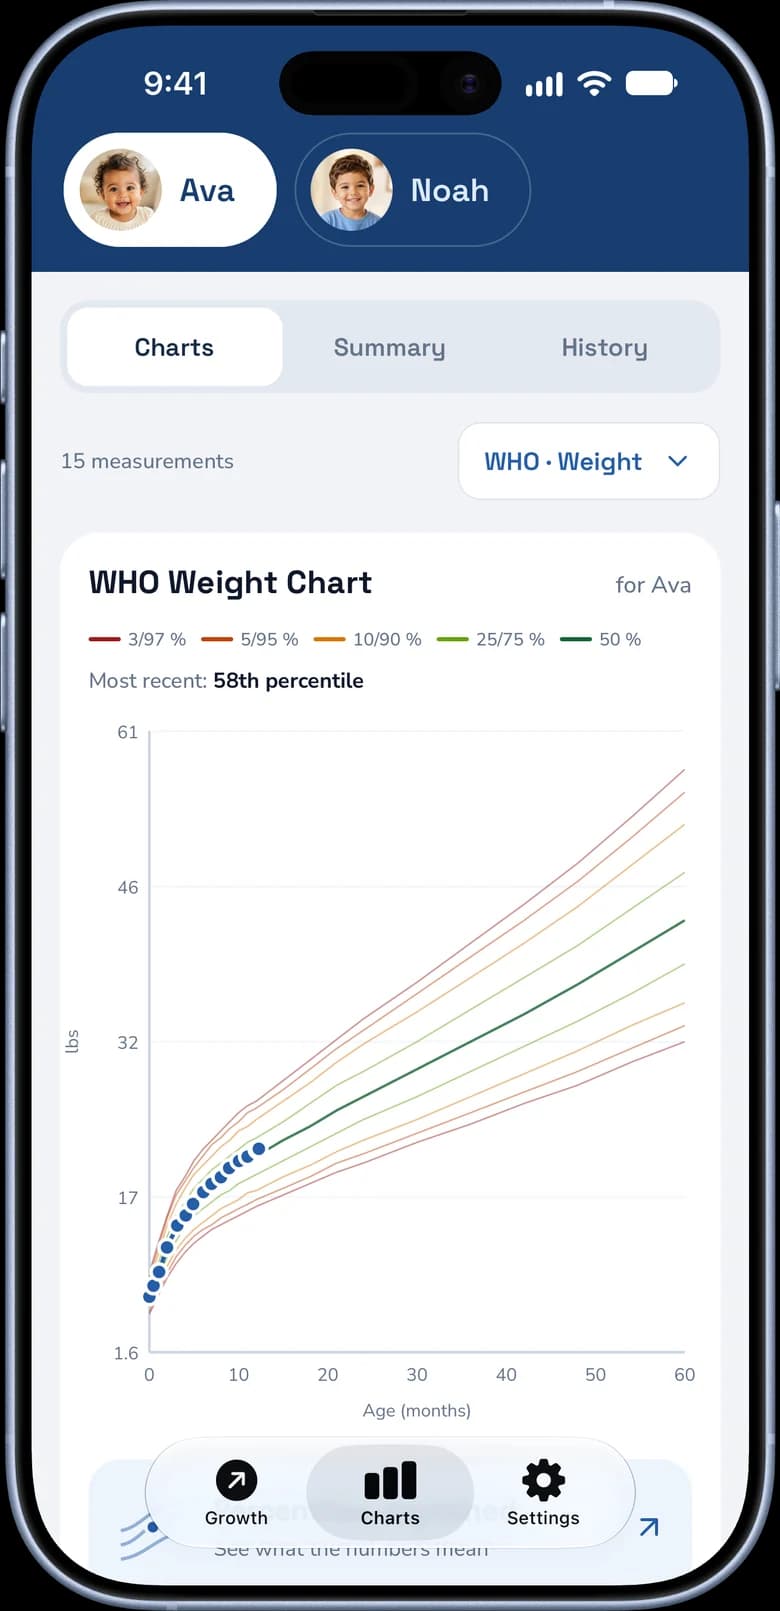
GrowthKit for iPhone
Plot every measurement on the WHO charts.
Percentiles, growth velocity and a PDF for your pediatrician. Free to download, with a free trial.

Prevention starts in infancy
Rapid weight gain in the first two years. In the UK's ALSPAC cohort, babies whose weight rose by more than 0.67 SD between birth and age 2, roughly crossing one major line upward on the WHO chart, were heavier and had more body fat at age 5 (Ong 2000). A meta-analysis of 10 cohorts (47,661 people) found that each +1 SD gain in weight between birth and age 1 doubled the odds of childhood obesity (Druet 2012).
This doesn't mean restricting feeds. Babies who were born small are expected to catch up, and growing babies need to eat to appetite. It means:
- Feed responsively. Watch for hunger cues (hands to mouth, lip smacking, later reaching for food) and fullness cues (closing the mouth, turning away, pushing food away), and let your child decide how much to eat (CDC). With bottles, that means not encouraging your baby to finish the last ounce once they've stopped.
- Don't use food as a reward or to soothe non-hunger distress. The CDC notes food is not a good reward or punishment.
- Watch the curve, not the scale. If your baby's weight is climbing across major percentile lines, or weight-for-length is above the 97.7th percentile, raise it with your pediatrician rather than cutting back on your own. Our guide to babies who are always in a high percentile explains when a big baby is simply big.
Breastfeeding may help modestly. In a large meta-analysis, breastfed people had lower odds of overweight or obesity later, but in the 11 highest-quality studies the reduction was about 13% (Horta 2015). Formula-fed babies benefit from the same responsive feeding.

Free tool
Baby Weight-for-Length Calculator
Check whether your baby's weight is in proportion to their length on the WHO standards, the measure used before age 2.
What works at home
1. Responsive eating, without pressure
Keep feeding responsive as your child grows. You decide what food is offered, when and where; your child decides whether to eat and how much. For typical amounts by age, see how many calories children need. Pressure to "clean the plate," bribes with dessert, and comments on how much a child eats all work against a child learning to stop when full.
2. Enough sleep
The American Academy of Sleep Medicine's consensus, endorsed by the AAP, says insufficient sleep increases the risk of obesity, as well as hypertension, diabetes and depression (AASM 2016).
| Age | Recommended sleep |
|---|---|
| 4–12 months | 12–16 hours |
| 1–2 years | 11–14 hours |
| 3–5 years | 10–13 hours |
| 6–12 years | 9–12 hours |
| 13–18 years | 8–10 hours |
Source: American Academy of Sleep Medicine consensus, 2016
3. Water and milk as the default drinks
The AAP recommends no juice before age 1, no more than 4 oz of 100% juice a day at ages 2–3 and 4–6 oz at ages 4–5. It advises avoiding sodas, sports drinks, fruit drinks, sweetened water and flavored milk (AAP, HealthyChildren.org). Whole fruit is better than juice at every age. Water and plain milk (whole milk at 12–24 months, then low-fat or nonfat) should be the everyday drinks.
4. Active play every day
- Under 1: floor play, including at least 30 minutes of tummy time a day for babies who aren't yet mobile (WHO 2019).
- Ages 1–4: at least 180 minutes a day of physical activity of any intensity; from age 3, at least 60 minutes of that should be moderate to vigorous (WHO).
- Ages 6–17: 60 minutes or more of moderate-to-vigorous activity every day, with vigorous, muscle- and bone-strengthening activity at least 3 days a week (CDC).
None of this needs organized sport. Running around outside, playgrounds, dancing and walking or biking to school all count. See does exercise affect child growth for more on activity at different ages.
5. Less screen time
WHO recommends no sedentary screen time for babies and 1-year-olds, and no more than 1 hour a day at ages 2–4 (less is better). Screens displace active play and sleep, especially in bedrooms at night.
6. Change habits as a family
Make changes for the whole household: regular family meals, cooking at home when you can, keeping sugary drinks out of the house, and screen rules that apply to adults too. The most effective treatment the AAP describes for children who already have obesity is family-based, which is a good model for prevention as well.
If your pediatrician raises weight concerns
Your pediatrician will look at your child's BMI percentile and its trend (see our guide to child BMI percentiles), plus family history, blood pressure, eating, activity and sleep. For children with obesity (BMI at or above the 95th percentile), the AAP's 2023 clinical practice guideline (Hampl 2023) recommends:
- Intensive health behavior and lifestyle treatment (IHBLT): 26 or more hours of face-to-face, family-based, multicomponent treatment over a 3- to 12-month period.
- Medication: pediatricians should offer adolescents 12 and older with obesity weight-loss medication, as an add-on to health behavior and lifestyle treatment. This applies to obesity, not only severe obesity.
- Surgery: teens 13 and older with severe obesity (BMI at least 120% of the 95th percentile) should be evaluated for metabolic and bariatric surgery.
The AAP says there's no evidence that "watchful waiting" or delaying treatment is appropriate for children with obesity.
Free tool
Child BMI Calculator
Calculate your child's BMI and CDC BMI-for-age percentile, and see which category it falls in.
A note on language
Children absorb how adults talk about bodies. The AAP describes obesity as a common chronic disease that has been stigmatized for years, and children and teens feel that stigma keenly. At home, talk about habits rather than weight:
- Vegetables help your body grow strong, not "so you don't get fat."
- Moving is for fun and energy, not for burning calories.
- Sleep helps your brain and mood, not your weight.
Avoid commenting on your child's body or putting them on a diet. If you're worried, take it to your pediatrician, and keep track of height and weight over time so the conversation is about the trend. GrowthKit plots your child's measurements on growth charts and calculates BMI-for-age percentiles (CDC, from age 2), which makes a gradual climb easier to spot. For more on reading those curves, see how to read a child growth chart.