To talk to your pediatrician about a growth concern, bring the numbers, describe exactly what changed, and leave with a plan. "She was around the 60th percentile for weight at 6 months and the 20th at 15 months" gets a far more useful answer than "I'm worried about her weight." Then ask what pattern would make the doctor want to look further, and when you'll check again.
Pediatricians judge growth mainly by the trend, not one measurement. Falling (or rising) across two major percentile lines is the usual trigger for a closer look (AAFP). This guide covers what to bring, a one-page summary you can fill in, the questions that get specific answers, and what to do if you feel brushed off.
What your pediatrician is looking at
Knowing what the doctor weighs helps you frame your concern in the same terms:
- The trend across visits. Is your child following roughly the same percentile line? Some shifting is common in the first two years; after age 2, most healthy children stay on their line (AAFP).
- Unusually low or high values. On the WHO charts used under age 2, the CDC recommends the 2.3rd and 97.7th percentiles (printed as the "2nd" and "98th" lines) as the cutoffs for unusually low or high growth (CDC).
- Weight compared with length or height. A child whose weight drops while length holds steady looks different from one who is small all over.
- Growth rate. In older children, how many centimeters they've grown in a year.
- The family. Parents' heights and when they went through puberty.
Weight and length or height are measured at every well-child visit, and head circumference at every visit through 24 months (Bright Futures). For how to read the chart yourself, see how to read a child growth chart.
GrowthKit for iPhone
Plot every measurement on the WHO charts.
Percentiles, growth velocity and a PDF for your pediatrician. Free to download, with a free trial.

What to gather before the visit
| What | Where to find it | Why it matters |
|---|---|---|
| Past measurements with dates | After-visit summaries, patient portal, baby book, school nurse | Shows the trend, not a snapshot |
| Home measurements, labeled as home | Your notes or app | Fills the gap between visits |
| Birth weight and gestational age | Hospital discharge papers | Preterm babies are plotted by corrected age through age 2 (AAP) |
| Both parents' heights | Measured, not guessed | Sets the family's expected range |
| How your child eats | A few typical days written down | Helps judge intake |
| Recent illnesses, medicines, big changes | Your memory and the medicine cabinet | Illness can cause a temporary dip |
| Other symptoms | Your observations | Energy, stools, development and sleep give context |
If you've been tracking at home, our guide to sharing baby growth data with your pediatrician covers how to export and present a growth chart.
A one-page growth summary you can fill in
Doctors can take in a short, structured page in a minute. Copy this outline into a note or print it, fill it in, and hand it over at the start of the visit.
1. About your child
- Name, date of birth, sex
- Born at ___ weeks; birth weight ___
- Ongoing conditions or medicines
2. Measurements (newest last; mark home measurements with "H")
| Date | Age | Weight | Length or height | Head | Where |
|---|---|---|---|---|---|
3. What changed, and when (one or two sentences)
4. Eating, sleep and energy (a typical day)
5. Other symptoms or recent illnesses
6. Family
- Mother's height ___, father's height ___
- Anyone who was a "late bloomer," very short, or had celiac or thyroid disease
7. My question today (one sentence)
Here's what section 2 and 3 look like for a toddler girl whose weight has been drifting:
| Date | Age | Weight | Length | Where |
|---|---|---|---|---|
| March | 6 months | 7.5 kg | 66.5 cm | Office |
| June | 9 months | 8.0 kg | 70.6 cm | Office |
| September | 12 months | 8.4 kg | 74.5 cm | Office |
| December | 15 months | 8.7 kg | 78.0 cm | Office |
What changed: her weight went from about the 59th percentile at 6 months to the 21st at 15 months, while her length stayed near the 57th. She's crossed two major weight lines over nine months, and her weight is falling behind her length.
That one sentence tells the doctor exactly what to look at. Our baby dropped on the growth chart guide explains the common reasons for a pattern like this.

Free tool
Pediatrician Visit Question Builder
Build a short, prioritized list of questions to take to your child's next appointment.
Questions that get specific answers
Open questions ("Is she growing okay?") invite reassurance. Focused ones invite a plan.
About the chart
- "Can you show me her growth chart? Which lines has she crossed, and over how long?"
- "Is her weight in proportion to her length or height?"
About causes
- "Could this be family genetics? Here are our heights."
- "Is there anything in her eating, illnesses or other symptoms that could explain it?"
- "Is there anything you'd want to test for now?"
About the plan
- "What change would make you want to do more?"
- "When should we recheck, and should that be on the office scale?"
- "At what point would you refer us to a specialist?"
That last question is often the most useful. It gets the doctor to say the threshold out loud, so you both know what you're watching for. For routine checkups, see questions to ask at every well-child visit.
If you feel dismissed
Short visits and different communication styles happen. If you leave without a clear answer, you have options:
- Book an appointment just for growth. Say when you call that it's to discuss growth, so time is set aside.
- Ask for the chart. Most practices can print the growth chart or let you download it from the portal.
- Be specific about what you're asking. "I'd like us to agree on a plan for her weight" is easier to act on than general worry.
- Ask directly for a referral if your concern meets the thresholds below.
- Get a second opinion if you've raised the same concern at two visits and still have no plan.
When to push for a faster appointment or referral
| What you notice | What to ask for |
|---|---|
| Newborn not back to birth weight by 2 weeks | Call now (AAP) |
| Weight loss outside a short illness, or a baby who isn't feeding well | Call the same day |
| Weight or height falling across two major percentile lines | A visit to review the chart and agree on a plan (AAFP) |
| Growing less than about 5 cm (2 in) a year before puberty | Ask about a referral (AAFP) |
| Predicted adult height more than about 10 cm (4 in) below the parents' target | Ask about a referral (AAFP) |
| No signs of puberty by 14 in boys or 13 in girls | Ask about a referral (AAFP) |
| Signs of puberty before 8 in girls or 9 in boys | Call and book a visit; see precocious puberty signs |
For what happens at a specialist visit, see when to see a pediatric endocrinologist for growth. For weight-specific red flags in babies, see when to worry about baby weight.
After the appointment
Send a short portal message to confirm the plan: "Just confirming: we'll recheck her weight on the office scale in 6 weeks, and you'll refer us if she's dropped further." It creates a record and makes sure you left with the same understanding.
If you're given a referral, book it before you leave or as soon as you get home. Pediatric specialists often have long waits.
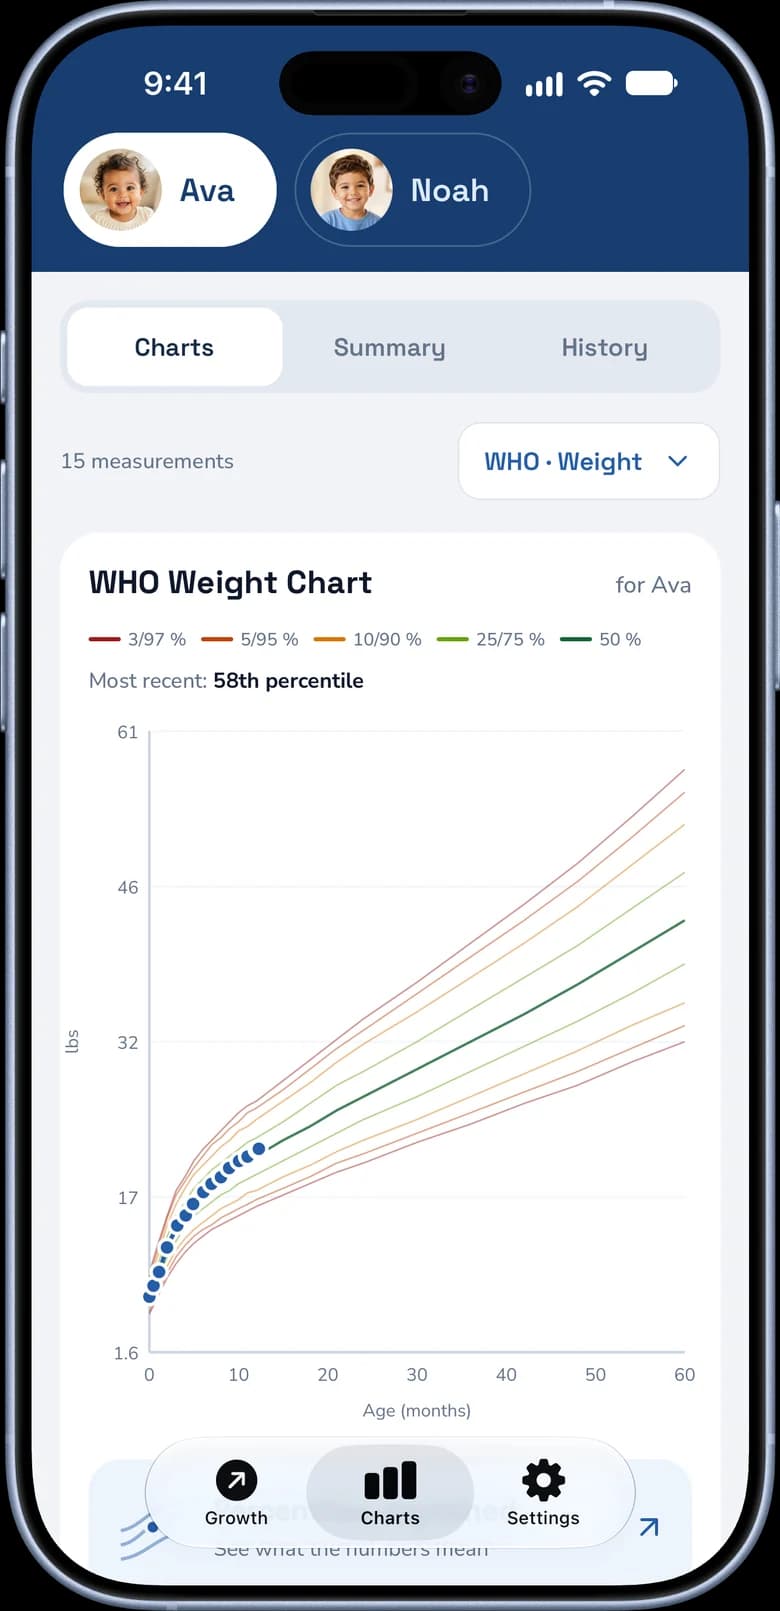
Between visits, measure the same way each time and keep everything in one place. In GrowthKit, the iPhone app we make, each measurement is plotted on WHO percentile charts, you can add a note to any entry ("measured at home," "after a stomach bug"), and you can export a PDF report to bring to the next visit. Office measurements remain the reference: their equipment is calibrated and staff are trained to use it (AAP).

Free tool
Baby Weight Percentile Calculator
Check your baby's exact WHO weight percentile before the visit.