


Failure to thrive (FTT) means a baby isn't gaining weight as expected. There's no single definition, but it usually means weight (or weight-for-length) below the 5th percentile for age and sex, or weight that falls across two major percentile lines over time (AAFP). It describes a growth pattern, not a disease and not a verdict on your parenting. Most babies respond well once the cause is found.
If you're worried right now, our growth concern red flags checker walks through which patterns need a call today and which can wait for the next visit. The rest of this guide explains what counts as FTT, what it looks like on a chart, the common causes, what the evaluation involves and when to call.
What counts as failure to thrive?
Doctors use a few overlapping measures. None is perfect on its own, which is why the AAFP stresses that valid weights over time, not a single number, are needed to recognize FTT (AAFP).
| Measure | What it means |
|---|---|
| Weight-for-age below the 5th percentile | Very low weight for age and sex (using corrected age for babies born early) |
| Weight-for-length below the 5th percentile | Thin for the baby's own length, not just small overall |
| Weight falls across two major percentile lines | A sustained slowdown from the baby's established curve |
| Weight gain well below the expected rate for age | Grams per day well under the normal range (see below) |
Source: American Family Physician, Failure to Thrive (2016).
A note on the charts. US pediatricians use the WHO charts from birth to age 2. On those charts the CDC recommends the 2.3rd percentile (printed as the "2nd" line) as the cutoff for unusually low growth (CDC MMWR). So a baby can be below the 5th percentile but above the 2nd line. That's one reason doctors look at the trend and the whole baby, not one cutoff. For how these cutoffs map to standard deviations, see what a z-score means on a growth chart.
The AAFP calls FTT a clinical finding rather than a diagnosis, and notes that the term "weight faltering" is perceived as less alarming. You may hear either term.
GrowthKit for iPhone
Plot every measurement on the WHO charts.
Percentiles, growth velocity and a PDF for your pediatrician. Free to download, with a free trial.

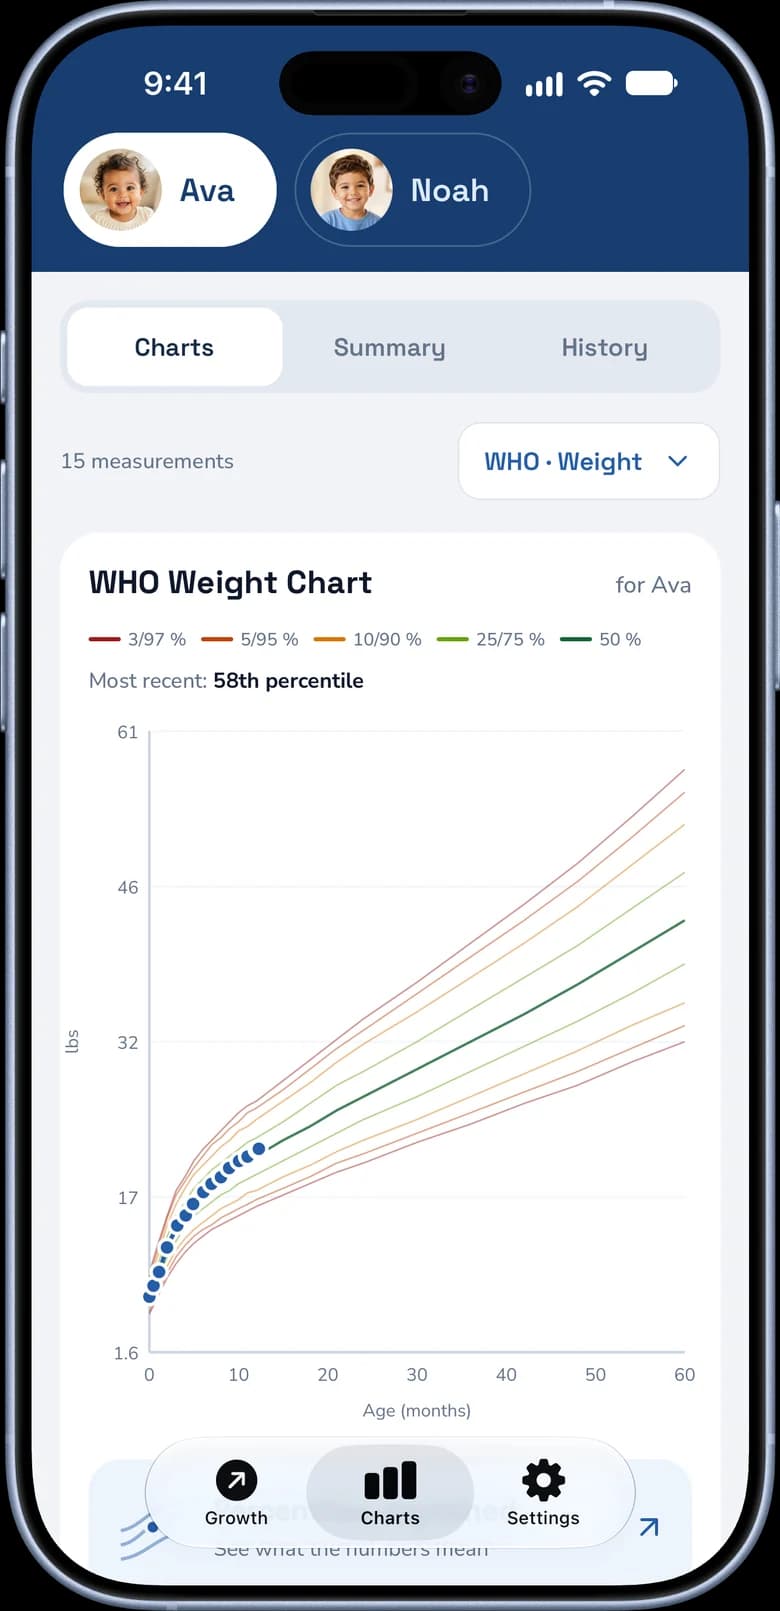
What failure to thrive looks like: a worked example
A baby who has always followed a low line, gains steadily and is developing well is usually just small. A baby who drops away from their own line is different. Here's an example girl:
- Birth: 3.2 kg, about the 47th percentile
- 2 months: 5.1 kg (48th percentile). Right on track.
- 3 months: 5.5 kg (31st percentile)
- 4 months: 5.7 kg (17th percentile)
- 5 months: 5.85 kg (9th percentile)
- 6 months: 5.95 kg (5th percentile)
Weight-for-age, girls, birth to 12 months
From 2 to 6 months she gained 850 g (about 30 oz) in roughly 120 days, about 7 grams a day. Babies typically gain a median of 17–18 g a day between 3 and 6 months (AAFP). She has fallen across two major percentile lines (the 25th and the 10th) and is now near the bottom of the normal range. That pattern is worth a prompt visit, well before her next routine checkup. The WHO also publishes weight velocity standards that doctors can use to judge gain directly.
For more on this pattern, see why babies fall off the growth curve and our baby weight gain per month chart. To see how far from the median your baby's weight sits, work out their WHO z-scores.

Free tool
Baby Weight Percentile Calculator
Enter your baby's age, sex and weight to see their WHO percentile at each weigh-in.
What causes failure to thrive?
The AAFP groups causes into three buckets. The most common by far is the first.
| Type | Examples |
|---|---|
| Not taking in enough calories (most common) | Poor latch or low milk supply, formula mixed incorrectly, reflux, feeding difficulties such as cleft lip or palate, weak suck or poor coordination, feeding routines that don't meet the baby's needs |
| Not absorbing enough | Milk protein allergy, celiac disease (once gluten is eaten), cystic fibrosis, liver and pancreas conditions, inherited metabolic disorders |
| Needing more energy | Congenital heart disease, chronic lung disease of prematurity, chronic infections, kidney failure, hyperthyroidism |
Source: AAFP (2016), Table 1.
Often more than one factor is involved. A baby with reflux may eat less because feeds are uncomfortable. Family circumstances matter too: the AAFP identifies poverty as the most significant psychosocial risk factor, which is why a good evaluation also asks about access to food, formula and support.
Signs parents may notice
Babies are weighed at every well visit, but parents often notice changes first:
- Feeds that are consistently short, tiring or followed by crying
- Fewer wet diapers. After the first 4–5 days, expect at least 5–6 a day (AAP).
- Clothes and diapers fitting more loosely, or loss of the chubby folds your baby used to have
- A baby who seems sleepier, less alert or less interested in play than before
- Development that seems to stall
In newborns, the AAP's warning signs are not being back to birth weight by about 2 weeks, or not gaining at least 5–7 oz a week after that (HealthyChildren). Most babies regain birth weight by about 2 weeks, and almost all by 3 weeks (HealthyChildren).
What the evaluation looks like
Most babies are evaluated as outpatients over a few visits:
- Confirm the pattern. Accurate weights and lengths, plotted on the right chart (by corrected age for babies born early; see the premature baby growth chart guide).
- A detailed feeding history. This is the most useful step: how often and how much the baby feeds, how formula is prepared, what solids are offered, stools and vomiting, and the family's routine and resources.
- A physical exam for signs of an underlying condition.
- Targeted tests, if any. The AAFP says no standard set of tests is recommended, and routine lab testing is rarely needed. Reasonable first tests, when used, include a blood count, urinalysis and electrolytes. Other tests are chosen to match a suspected cause: for example, celiac blood tests once gluten is in the diet, or a sweat test if cystic fibrosis is suspected.
Treatment and catch-up growth
Treatment depends on the cause (AAFP):
- Feeding support for the most common cause, inadequate intake. Lactation help with latch and supply, more frequent feeds, checking formula preparation and amounts, and help with solids.
- Extra-calorie feeds such as more concentrated formula, only as directed by your pediatrician or dietitian. Never change how you mix formula on your own.
- Treating any underlying condition, alongside nutrition support.
- Regular weight checks. Follow-up ranges from weekly to every few months, and infants need closer follow-up than older children. Daily weights are discouraged because they jump around; gain is judged over days to weeks.
Catch-up growth happens when a child gains at two to three times the average rate for their age. Hospital admission is rarely needed. It is considered for severe malnutrition or dehydration, a serious underlying illness, safety concerns, or when intensive outpatient treatment hasn't worked after 3–4 months (sooner for newborns).
When to call your pediatrician
Young babies have less reserve, so act faster under 6 months.
| Situation | What to do |
|---|---|
| Very sleepy or hard to wake, very few wet diapers (urinating only 1–2 times a day), sunken eyes or soft spot | Seek care now (HealthyChildren) |
| Green (bile-colored) vomit | Seek care immediately (HealthyChildren) |
| Newborn not back to birth weight by 2 weeks, or gaining less than 5–7 oz a week after that | Call your pediatrician now |
| Under 6 months: no weight gain between weigh-ins 1–2 weeks apart, fewer than 5–6 wet diapers a day, or feeds getting shorter or refused | Call within a day or two; don't wait a week |
| 6 months or older: no weight gain over a month | Call and book a weight check within a week |
| Weight has fallen across two major percentile lines | Book a visit soon |
| Weight follows a steady low line, and your baby feeds well and is developing normally | Usually fine; keep weighing at well visits |
For more help deciding, see when to worry about baby weight. If your child is past the baby stage, see toddler not gaining weight. For what recovery looks like, see catch-up growth.

Free tool
Growth Concern Red Flags Checker
Review the growth patterns that suggest it's time to talk to your pediatrician, with clear thresholds.



