See a pediatric endocrinologist when your child's growth pattern, not just their height, looks abnormal. The usual triggers are height below the 3rd percentile, a growth rate that is slow for your child's age, falling across two major percentile lines, a predicted height more than 5 cm (2 in) away from what the parents' heights suggest, or puberty that starts very early or very late (AAFP). In the US, the referral usually goes through your pediatrician.
Most children who see an endocrinologist for growth turn out to be healthy and simply short or late to develop. The visit is about finding the few who have a treatable cause. This guide covers when to ask for a referral, which growth rates are slow at each age, and how to put together a referral packet that makes the first appointment count.
Short vs. a growth problem
Pediatricians separate three broad groups (AAFP; StatPearls):
- Familial short stature. Short parents, normal growth rate, bone age normal for age. The child follows a low line and ends up short like the family.
- Constitutional delay of growth and puberty ("late bloomer"). Normal growth rate for a delayed "internal clock," bone age behind actual age, late puberty, normal adult height in the end. It is the most common cause of delayed puberty (AAFP, 2017).
- Pathologic short stature. A medical cause, such as growth hormone deficiency, hypothyroidism, celiac disease, Turner syndrome, chronic illness or medicines. The growth rate is usually slow and the child falls further behind over time.
Most children evaluated for short stature fall into the first two groups. Our guide to short stature in children explains these patterns in depth.
Referral triggers
| Trigger | Details |
|---|---|
| Very short or very tall | Height below the 3rd percentile or above the 95th percentile for age and sex |
| Slow (or fast) growth rate for age | A yearly growth rate outside the normal range for age, even if height is still in the normal range |
| Crossing percentile lines | Falling across two major percentile lines, or any crossing of lines after age 2 |
| Off the family's target | Projected adult height more than 5 cm (2 in) from the mid-parental target |
| Unusual features | Several syndromic or unusual physical features |
| Bone age far off | Bone age advanced or delayed by more than 2 standard deviations |
| Early puberty | Signs of puberty before age 8 in girls or before age 9 in boys |
| Late puberty | No breast development by 13 in girls; no testicular growth by 14 in boys |
Sources: AAFP, Short and Tall Stature (2008), Table 4; puberty ages from AAFP, Disorders of Puberty (2017).
Under age 2, some shifting across percentiles is common as babies settle onto their genetic line. After age 2, most healthy children stay close to their line, so crossing lines matters more (AAFP). For early puberty specifically, see signs of precocious puberty.
GrowthKit for iPhone
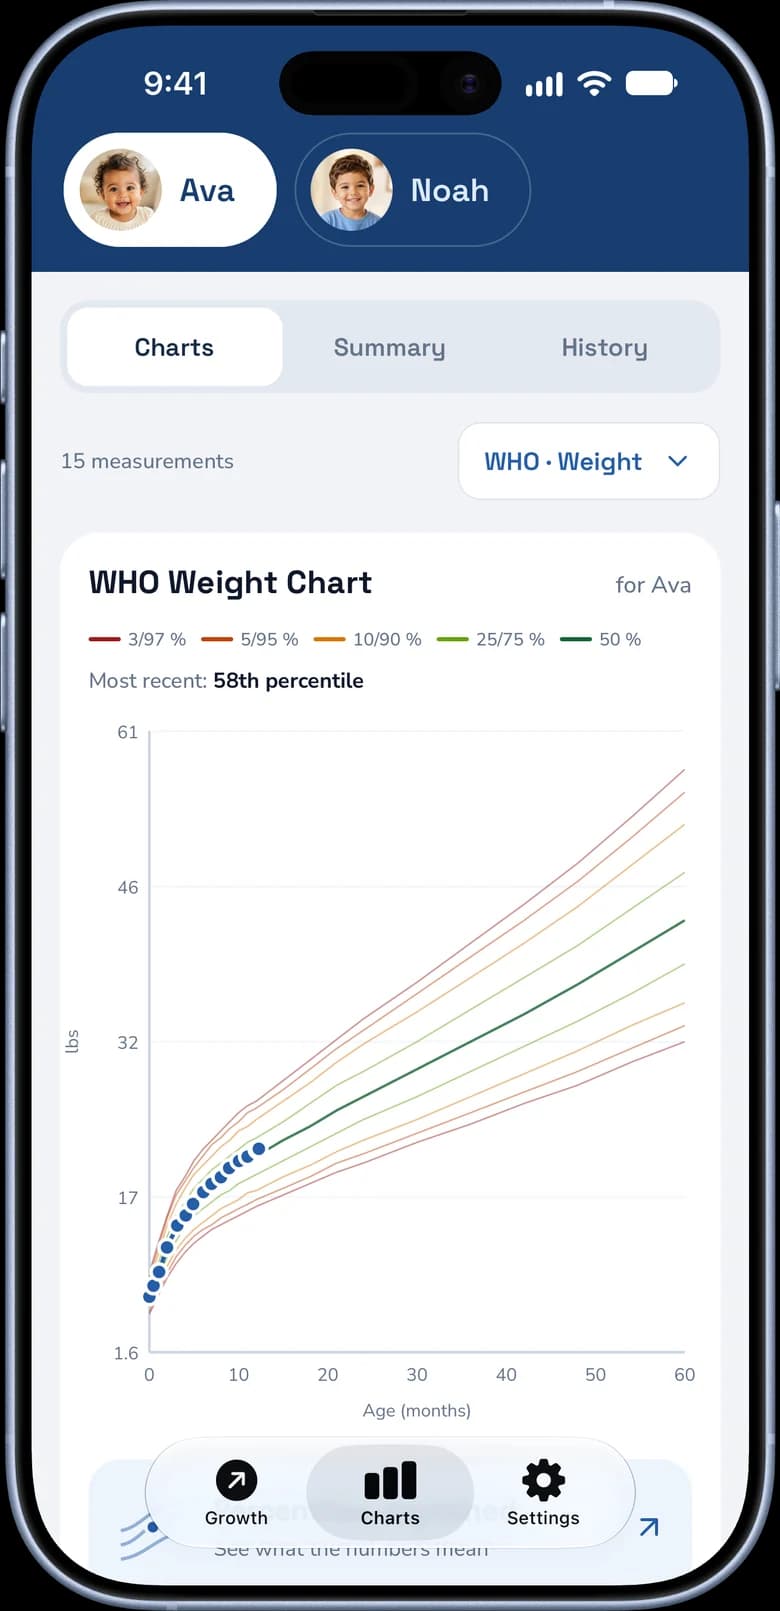
Plot every measurement on the WHO charts.
Percentiles, growth velocity and a PDF for your pediatrician. Free to download, with a free trial.

Growth rate: the number that matters most
A child at the 10th percentile who grows 6 cm a year at age 7 is growing normally. A child at the 50th percentile who grows 3 cm a year at the same age has a problem, even though their height still looks average. The catch is that "normal" changes a lot with age (AAFP):
| Age | Normal growth per year | What counts as slow |
|---|---|---|
| Second year (12–24 months) | 10–14 cm (4–6 in) | Clearly under 10 cm |
| Fourth year (about 3–4 years) | 6–7 cm (2–3 in) | Under about 6 cm; 5 cm is already slow here |
| School age, before puberty | 5–5.5 cm (about 2 in) at the slowest point | Persistently under about 4–5 cm |
| Puberty growth spurt | Girls 8–12 cm; boys 10–14 cm | No spurt by the ages in the puberty row above |
Normal ranges: AAFP (2008), Table 1. The "slow" column compares a full year of growth with the bottom of each normal range; your pediatrician will interpret it with the whole picture.
A single cutoff such as "under 4 cm a year" is too low for young children: a 3-year-old growing 4.5 cm a year is well below the normal 6–7 cm. Use measurements taken at least 6 months apart (ideally 12), because over shorter gaps normal measuring error can be as big as the growth itself.

Free tool
Height Growth Velocity Calculator
Turn two dated height measurements into a yearly growth rate for your pediatrician.
What to bring: an example referral packet
Endocrinologists work from growth data. A short, organized packet saves time and can shorten the path to an answer. Here is an example for a girl referred at age 8:
Growth record (all measured on the pediatrician's stadiometer, plotted on CDC charts):
- Age 6 y 0 m: 111.0 cm, about the 23rd percentile
- Age 7 y 0 m: 116.0 cm, about the 15th percentile
- Age 8 y 0 m: 119.5 cm, about the 8th percentile
Growth rate calculation:
- Age 6 to 7: 116.0 − 111.0 = 5.0 cm in 12 months, or 5.0 cm a year (low-normal)
- Age 7 to 8: 119.5 − 116.0 = 3.5 cm in 12 months, or 3.5 cm a year (slow for age)
Family target: mother 160 cm, father 175 cm. For a girl, the mid-parental target is (160 + 175 − 13) ÷ 2 = 161 cm, with most adult heights within about 8 cm of it. Our adult height predictor guide explains the formula.
Checklist for the packet:
- Every dated height and weight you have (clinic records first; school or home measurements marked as such)
- A plotted growth chart, or a printout from your pediatrician
- The growth rate for each 6–12-month interval, worked out as above
- Both parents' measured heights, and when each parent went through puberty (age at first period, or a late growth spurt in a father)
- Birth weight, length and gestational age
- Long-term illnesses and all regular medicines, including asthma inhalers, steroids and ADHD medicines
- A short description of diet and appetite, and any digestive symptoms
- Copies of any blood tests or X-rays already done
If you log measurements in GrowthKit, its PDF report and height-velocity chart can go straight into the packet. Your pediatrician will re-plot clinic heights on the chart they use: WHO charts under 2 and CDC charts from age 2 in the US (CDC). For more on getting data to your doctor, see how to share your baby's growth data with your doctor.
What happens at the first visit
History and exam. Expect questions about pregnancy, birth, illnesses, medicines, diet, family heights and puberty timing. The exam includes height, weight, sitting height and arm span (to check body proportions), and a puberty exam.
Bone age X-ray. An X-ray of the left hand and wrist shows skeletal maturity. Interpreting it (AAFP):
- Normal for age: typical of familial short stature
- Delayed, in line with the child's height: typical of constitutional delay, the healthy "late bloomer" pattern
- Severely delayed, with the gap widening over time: points to a medical cause such as growth hormone deficiency or hypothyroidism
- Advanced in a tall or fast-growing child: can point to early puberty
A delayed bone age is good news in one way: it means more growing time remains.
Blood and other tests. The workup is tailored to the child, but commonly includes:
- A basic screen: blood count, metabolic panel, inflammation marker and urinalysis
- Thyroid function: TSH and free T4
- Celiac screening: tTG-IgA plus a total IgA level. The total IgA matters because a child with low IgA can have a falsely negative tTG-IgA, in which case an IgG-based test is used (ESPGHAN 2020).
- IGF-1 and IGFBP-3 as a screen of the growth hormone system
- A chromosome test (karyotype) for short girls, since Turner syndrome can be subtle. The AAFP advises thyroid tests and a karyotype for all girls with short stature.
Growth hormone stimulation tests come later, only if the picture suggests growth hormone deficiency. They are imperfect, so results are read alongside the growth pattern (Grimberg et al., 2016). The full short-stature workup is explained in our short stature guide, and the hormone side in growth hormone deficiency in children.
Common outcomes
- A normal variant (familial short stature or constitutional delay): the most common result. Often the plan is to keep measuring and recheck the growth rate.
- Growth hormone deficiency: treated with daily growth hormone injections. See growth hormone deficiency in children.
- Hypothyroidism: treated with a daily thyroid hormone pill. See thyroid problems and child growth.
- Celiac disease: treated with a strict gluten-free diet, often followed by catch-up growth. See celiac disease in children.
- Turner syndrome, puberty disorders or other conditions: managed long term, often with other specialists.
When to push for a referral
| Situation | What to do |
|---|---|
| Your child is short but has grown at a normal rate along the same line for years | Keep measuring at well-child visits; ask about the family target if you're unsure |
| A full year of growth is below the normal range for age | Ask your pediatrician to calculate the growth rate and discuss a referral |
| Height has fallen across two major lines, or crossed lines after age 2 | Ask for a referral |
| Puberty signs before 8 (girls) or 9 (boys), or none by 13 (girls) or 14 (boys) | Ask for a referral |
| A short girl with no clear cause | Ask about thyroid tests and a karyotype |
| Slowing growth together with new headaches, repeated vomiting or vision changes | Call your pediatrician the same day |
If your concern feels brushed aside, a specific question helps: "What was my child's growth rate over the last 12 months, and how does it compare with normal for their age?" Our guide to talking to your pediatrician about growth has more ways to keep the conversation moving.

Free tool
Growth Concern Red Flags
Check which growth patterns are worth raising with your pediatrician, and how soon.